

Select your medication or enter your Absolute Neutrophil Count (ANC) to assess risk and required actions.
Enter your lab values to calculate Absolute Neutrophil Count (ANC).
Imagine your body’s primary defense against bacteria simply vanishes. Not gradually, but overnight. This is the reality of agranulocytosis, a severe condition where your absolute neutrophil count (ANC) drops below 100 cells per microliter of blood. It sounds rare, but it’s a silent threat lurking in common prescriptions. Up to 70% of these cases are triggered by medications you might be taking right now.
Why does this matter? Because without neutrophils-the white blood cells that hunt down infections-a simple sore throat can spiral into sepsis within days. The mortality rate for untreated agranulocytosis hits 10-20%. But here’s the good news: with proper monitoring and quick action, that number drops to less than 5%. This guide breaks down which drugs carry the highest risk, how to spot the warning signs, and what monitoring protocols actually save lives.
Agranulocytosis is not just low immunity; it is a specific hematological emergency. To understand it, you need to look at your blood. Normally, your bone marrow produces neutrophils, a type of granulocyte. When certain drugs interfere with this process, production halts or existing cells are destroyed faster than they can be replaced.
The clinical definition is strict. While neutropenia refers to an ANC below 1,500/μL, agranulocytosis is the extreme end of the spectrum, defined as an ANC of less than 100/μL. At this level, your immune system is effectively offline. The onset isn’t always immediate. For most patients, symptoms appear 1 to 3 months after starting a new medication, though some reactions happen within days, while others take years to manifest.
Two main mechanisms drive this damage. About 60% of cases involve an immune-mediated reaction, where your body creates antibodies that attack its own neutrophils because they’re attached to the drug molecules. The remaining 40% result from direct toxicity, where the drug poisons the bone marrow precursors directly. Knowing which mechanism is at play helps doctors decide whether to stop the drug immediately or adjust the dose, though in severe cases, stopping is almost always the first step.
Not all drugs pose the same threat. Over 200 medications across 15 classes have been linked to agranulocytosis, but a handful stand out for their higher incidence rates. If you are prescribed any of these, rigorous blood testing isn’t optional-it’s mandatory.
Clozapine is the poster child for medication-induced agranulocytosis. Used for treatment-resistant schizophrenia, it carries an absolute risk of about 0.8%. That means roughly 1 in 125 patients will develop this condition. Because of this, the FDA mandates a Risk Evaluation and Mitigation Strategy (REMS) program, requiring weekly blood tests for the first six months. Skipping these checks is dangerous; studies show only 68% of prescribers strictly adhere to this schedule in the US.
Antithyroid drugs like propylthiouracil and methimazole also carry significant risk. Propylthiouracil has an incidence of 0.36 per 1,000 patient-years, making it more risky than methimazole (0.16 per 1,000). Patients treating hyperthyroidism should be especially vigilant if they develop a fever or mouth ulcers in the first few months of therapy.
Antibiotics are another major culprit. Trimethoprim-sulfamethoxazole (often known as Bactrim or Septra) increases the relative risk of agranulocytosis by 15.8 times compared to non-users. Other antibiotics like chloramphenicol and beta-lactams have also been implicated, though less frequently. Even over-the-counter painkillers aren’t entirely safe; dipyrone, a common analgesic in many countries, has a notable association, whereas ibuprofen shows minimal risk.
| Medication Class | Specific Agent | Risk Level / Incidence | Monitoring Requirement |
|---|---|---|---|
| Antipsychotic | Clozapine | ~0.8% (High) | Weekly CBC for 6 months, then biweekly/monthly |
| Antithyroid | Propylthiouracil | 0.36 per 1,000 patient-years | Baseline CBC, then as needed based on symptoms |
| Antibiotic | Trimethoprim-sulfamethoxazole | RR 15.8 vs non-users | Baseline CBC recommended for long-term use |
| Analgesic | Dipyrone | 1.2 per 10,000 patient-years | Periodic monitoring if used chronically |
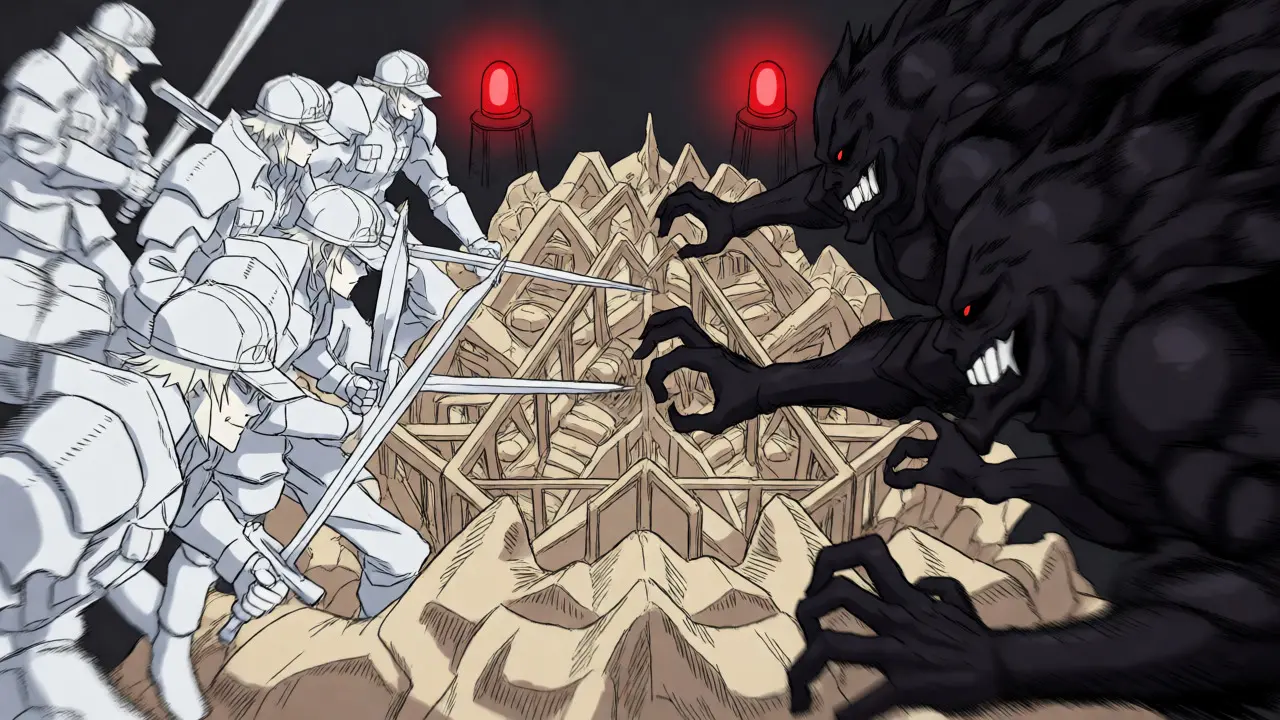
Time is tissue-and in this case, time is life. The early symptoms of agranulocytosis are often dismissed as minor viral illnesses, leading to fatal delays. A survey by the Aplastic Anemia & MDS International Foundation found that 86% of patients experienced diagnosis delays exceeding 48 hours. Why? Because the initial signs are vague.
The most common red flags are fever above 38.3°C (101°F) and sudden sore throat. You might also notice painful mouth ulcers, gum swelling, or skin abscesses. These aren’t just annoyances; they are signals that your neutrophil army has retreated. If you are on a high-risk medication and develop a fever, do not wait to see if it passes. Treat it as a medical emergency.
Other subtle signs include unexplained fatigue, chills, and slow-healing wounds. Because the immune system is compromised, even minor cuts can become infected quickly. Patients often report feeling "off" before the full-blown crisis hits. If you feel unusually weak or get sick repeatedly while on clozapine or antithyroid drugs, contact your doctor immediately. Don’t let a provider brush off your concerns as a cold. Demand a complete blood count (CBC).
Monitoring is the safety net that catches agranulocytosis before it kills. The cornerstone of management is regular measurement of the Absolute Neutrophil Count (ANC). For clozapine users, the protocol is rigid: weekly tests for the first 6 months, every two weeks for the next 6 months, and monthly thereafter. If the ANC drops below 1,000/μL, treatment must stop. Below 500/μL, it’s a critical alert.
But adherence is a problem. Only 68.3% of US prescribers follow the weekly monitoring rule during the critical first 18 weeks. In rural areas, access to labs is even harder, with 38% of cases reporting inconsistent laboratory access. This gap contributes to missed diagnoses. New technologies aim to close this divide. Point-of-care devices like the Hemocue WBC DIFF system, cleared by the FDA in 2022, can provide ANC results in five minutes rather than 24-48 hours. Studies show this improves adherence rates by over 30%.
If you are on Tier 1 high-risk medications, ensure your lab work is scheduled automatically. Don’t rely on memory. Set reminders. If you miss a test, reschedule it immediately. A single missed week could hide a dangerous drop in counts.
Once agranulocytosis is confirmed, the first step is discontinuing the offending drug. Dr. David C. Dale, a leading researcher in neutropenia, states that stopping the agent is the cornerstone of management. Recovery typically begins within 1 to 3 weeks after cessation, as the bone marrow recovers.
However, stopping the drug isn’t enough if an infection has already taken hold. Febrile neutropenia-fever combined with low neutrophils-is treated as a medical emergency. The Infectious Diseases Society of America recommends immediate broad-spectrum antibiotics, specifically covering Pseudomonas aeruginosa. This aggressive approach reduces mortality from 21% to 5.9% in clinical trials. Do not wait for culture results to start antibiotics.
In severe cases, doctors may administer Granulocyte-Colony Stimulating Factors (G-CSF), such as filgrastim, to stimulate bone marrow production of neutrophils. This accelerates recovery and shortens hospital stays. Once the ANC returns to safe levels, re-challenging with the same drug is usually avoided due to the high risk of recurrence. Alternative therapies must be explored, balancing psychiatric or thyroid control against hematological safety.
We are moving toward precision medicine in managing this risk. In 2023, the FDA approved the HLA-DQB1*05:02 assay, a genetic test developed by Genentech. This biomarker identifies patients with a 14.3-fold increased risk of clozapine-induced agranulocytosis. By screening for this genetic marker before starting treatment, clinicians can avoid prescribing high-risk drugs to vulnerable individuals.
Artificial intelligence is also playing a role. A 2022 study in JAMIA showed that AI-powered electronic health record alerts reduced missed agranulocytosis cases by 47%. These systems analyze patterns in lab data and medication history to flag risks before human eyes might catch them. As pharmacogenomic testing becomes more affordable, we expect pre-treatment genetic screening to become standard for high-risk medications by 2028.
Generally, yes, but caution is advised. Ibuprofen and acetaminophen are considered lower risk for agranulocytosis compared to dipyrone or certain NSAIDs. However, always check with your pharmacist or doctor before adding new medications, as interactions can affect blood cell counts or mask fever symptoms.
Recovery typically occurs within 1 to 3 weeks after discontinuing the offending medication. Bone marrow function resumes, and neutrophil counts rise back to normal levels. In severe cases, G-CSF injections may be used to speed up this process.
No, drug-induced agranulocytosis is usually reversible once the causative agent is removed. However, the condition itself is temporary, but the susceptibility to the specific drug remains. Re-exposure to the same medication often triggers a rapid and severe recurrence, so it is generally contraindicated for future use.
Seek immediate medical attention. Do not assume it is a common cold. Go to an urgent care or emergency department and explicitly state your medication list. Request a Complete Blood Count (CBC) to check your neutrophil levels. Delaying treatment for febrile neutropenia significantly increases mortality risk.
While nutrition supports overall immune health, no diet or supplement can reverse agranulocytosis caused by medication toxicity. Proper hydration, rest, and avoiding exposure to pathogens are crucial supportive measures, but medical intervention (stopping the drug and potentially using G-CSF) is required for recovery.



Venkatesan V.K.
Lazy reading of the stats here but the core point stands. Agranulocytosis is a hematological emergency not a minor inconvenience.
The mortality rate drop from 10-20% to under 5% with proper monitoring is the only metric that matters. Most patients ignore the fever warning signs until it is too late. This article correctly identifies that adherence to blood testing protocols is the primary failure point in clinical practice.
Marc-David Mayer
This is such important info! 🌟 So glad you highlighted the importance of checking for fever or sore throat immediately if you're on these meds. It's easy to dismiss them as a cold, but catching it early saves lives! 💪 Keep up the great work spreading awareness! ❤️
Patrick van der Velde
It is frankly appalling that we still rely on manual adherence to weekly CBC schedules when automated systems exist. The statistic that only 68% of prescribers follow the rule is indicative of a systemic failure in medical education and patient empowerment. We treat this condition reactively rather than proactively which is morally indefensible given the available technology. Patients are often left to navigate complex monitoring regimes without adequate support structures in place. This negligence contributes directly to preventable deaths in vulnerable populations who cannot advocate for themselves effectively in healthcare settings.
Stephen Horn
The data presented regarding Clozapine risk is accurate but lacks context regarding pharmaceutical lobbying influences on monitoring guidelines. One must consider why point-of-care devices like Hemocue were cleared so recently despite existing for decades. There is a clear pattern where cost containment strategies delay the implementation of life-saving diagnostics. Furthermore the genetic testing approval by Genentech raises questions about profit motives versus genuine public health priorities. We are seeing a shift towards personalized medicine but it remains accessible primarily to those with premium insurance coverage. This creates a two-tier system of safety for patients on high-risk medications.
hareesh kumar
i totally agree with the points made above especially about the conspiracy of big pharma hiding the true risks of common drugs like bactrim because they make billions off it while people die silently from agranulocytosis that could have been prevented if doctors actually cared more about their patients than their quotas and i think its insane that we still wait 24 hours for lab results when we have tech that can do it in 5 mins but they keep us waiting because maybe they want to sell more hospital beds or something idk but yeah scary stuff really makes you think twice before taking any pill prescribed by a doctor who barely looks at you during the visit
Gurjit Singh
The moral obligation of physicians to enforce strict monitoring cannot be overstated. Ignoring baseline CBCs for antithyroid drugs is negligent. Patients deserve transparency about the risks involved in treatment plans. Failure to act on early symptoms reflects poorly on the healthcare system's prioritization of patient safety over administrative convenience.
Harry Falk
Concise summary. Monitoring saves lives. Adherence is key.
Eryn Manchego
love this deep dive into neutrophil dynamics and the sheer vulnerability our immune systems face when bone marrow production gets hijacked by drug toxicity... it’s wild how a simple sore throat can signal such catastrophic cellular collapse yet we’re often told to just rest and hydrate... the shift toward HLA-DQB1*05:02 screening feels like a beacon of hope for precision pharmacology finally catching up to clinical reality... also props to the mention of G-CSF as a bridge therapy since waiting for spontaneous marrow recovery can feel like an eternity when you’re running a fever... keep shining light on these silent threats... ✨🩸💊
Lolo Del
Friendly reminder that dipyrone is banned in many countries for good reason. Don't let anyone tell you OTC painkillers are always safe. Check your local regulations and consult a pharmacist. Knowledge is power.
kishhore kumar
this is super useful info honestly i had no idea about the connection between methimazole and agranulocytosis until i read this
the part about the ANC dropping below 100 is terrifying though
does anyone know if there are specific supplements that help support bone marrow health alongside medication?
would love to hear thoughts from others who have dealt with this issue
thanks for sharing this detailed breakdown it helps demystify the jargon a bit
Morgan Law
Hey everyone, just jumping in to say this is a solid resource. If you're on clozapine or similar meds, please set those phone alarms for your blood tests. Seriously, don't skip them. The community here is great at supporting each other through the anxiety of waiting for results. Stay safe out there!
Sarah Leitschuh
I appreciate the balanced view here. While the risks are real, panic isn't helpful. Open communication with your provider about symptoms is crucial. Many patients fear being labeled 'drug-seeking' or 'anxious' when reporting side effects, so validating these concerns is vital. Let's keep the dialogue constructive and focused on actionable steps for safety.
Aaron Gragg
From a cultural perspective, the stigma surrounding psychiatric medications in many communities exacerbates the non-adherence rates mentioned in the text. Patients often discontinue clozapine due to social pressure rather than medical necessity, leaving them vulnerable to relapse and potentially complicating future treatment options. Furthermore, the explanation of immune-mediated versus direct toxicity mechanisms is critical for understanding why re-challenge is contraindicated. It is not merely about dose adjustment; the body remembers the antibody response. Therefore, thorough patient education regarding the irreversibility of sensitization is paramount for long-term management success.
Curtis Surpless
contrarian take here but most of this is standard med school 101 stuff disguised as breaking news
the real issue isn't lack of knowledge it's systemic inefficiency and bureaucratic inertia preventing widespread adoption of point-of-care testing
we already know the risks we just haven't fixed the workflow
also calling ibuprofen minimal risk is misleading given recent studies on NSAID-induced cytopenias
nuance matters
don't oversimplify hematology
keep it real